Your shopping cart is empty!
Welcome visitor you can login or create an account.
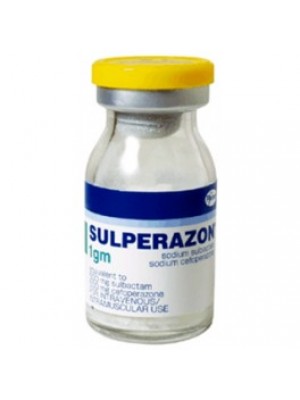
SULPERAZONE 1 g.
Product Code: SULPERAZONE 1 g.
Availability: In Stock

Product viewed: 2127


SULPERAZONE 1 g.
QUALITATIVE AND QUANTITATIVE COMPOSITION
Sulbactam sodium / cefoperazone sodium dry powder for solution for injection, which comes as a mixture of sulbactam and cefoperazone is 1: 1 ratio (SBT / CPZ).
Sulbactam is a derivative of the basic penicillin nucleus. It is an irreversible beta-lactamase inhibitor for parenteral use. In chemical nature is sodium penitsilat sulfone. One gram contains 92 mg of sodium (4 mEq). Sulbactam is an off-white crystalline powder with high water solubility. The molecular weight is 255.22.
Cefoperazone sodium is a semisynthetic broad-spectrum cephalosporin antibiotic for parenteral administration. One gram contains 34 mg of sodium (1.5 mEq). Cefoperazone is a white crystalline powder that is freely soluble in water. The molecular weight is 667.65.
3. PHARMACEUTICAL FORM
The vials contain equivalent amounts sulbactam and cefoperazone 1000 mg + 1000 mg.
4. CLINICAL DATA
4.1. indications
monotherapy
Sulbactam / cefoperazone is indicated for the treatment of severe infections requiring parenteral treatment with the combination of sensitive microorganisms:
- Respiratory tract infections (upper and lower);
- Urinary tract infections (upper and lower);
- Peritonitis, cholecystitis, cholangitis and other intra-abdominal infections;
- Septicemia;
- Meningitis;
- Skin infections and infections of the soft tissues;
- Bone and joint infections;
- Pelvic inflammatory disease, endometritis, gonorrhea and other infections of the reproductive system.
combination therapy
Because of the wide range of sulbactam / cefoperazone, most infections can be treated adequately with this antibiotic alone. However, sulbactam / cefoperazone may be used concomitantly with other antibiotics if such combinations are shown.
If used in conjunction with an aminoglycoside (see. Section 6.2. Incompatibilities - Aminoglycosides), renal function should be monitored during treatment (see. Section 4.2. Dosage and method of administration - Use in renal failure).
4.2. Dosage and method of administration
Use in adults
The daily dose is divided into two equal parts in 12 hours.
In severe or refractory infections the daily dose of sulbactam / cefoperazone may be increased to 8 g of 1: 1 ratio (ie the activity of cefoperazone - 4 g). May require additional cefoperazone administered separately in some patients, of which the ratio 1: 1. The daily dose should be administered 12 hours, divided into equal parts.
The recommended maximum daily dosage of sulbactam is 4 g.
Use in liver failure
See. Section 4.4. Special warnings and precautions for use.
Use in renal failure
In patients with significantly reduced renal function (creatinine clearance <30 ml / min) is necessary to adjust the dosing regimen to compensate for the reduced clearance of sulbactam. In patients with creatinine clearance between 15 and 30 ml / min should receive a maximum of 1 g sulbactam every 12 hours (maximum daily dose - 2 g sulbactam), while patients with creatinine clearance below 15 ml / min should receive a maximum of 500 mg sulbactam 12 hours (maximum daily dose of -1 g sulbactam). In severe infections may be necessary to administer additional cefoperazone.
The pharmacokinetic profile of sulbactam is significantly altered by hemodialysis. Serum half-life of cefoperazone is reduced slightly during hemodialysis. Therefore the product should be administered after dialysis.
Use in the elderly
See. Section 5.2. Pharmacokinetic properties.
Use in children
The daily dose should be administered every 6 to 12 hours, divided into equal parts.
In severe or refractory infections, these doses may be increased to 160 mg / kg daily from 1: 1 ratio (ie the activity of cefoperazone - 160 mg / kg daily). The daily dose should be npi 2 to 4 equal parts (see. Section 4.4. Special warnings and precautions for use - Use in children and section 5.3. Preclinical safety data - Use in children).
Use in infants
In neonates one week of age to the product should be administered 12 hours. The maximum daily dose of sulbactam in children should not exceed 80 mg / kg daily (see. Section 4.4. Special warnings and precautions for use - Use in infancy).
intravenous
For intermittent intravenous infusion, each vial sulbactam / cefoperazone should be reconstituted with the appropriate amount (see. Section 6.6. Application Instructions - Dilution) 5% aqueous glucose solution, 0.9% sodium chloride for injection, or sterile water for injection and then diluted to 20 ml with the same solution, and then applied for 15 to 60 minutes.
Ringer's lactate solution is an appropriate means of intravenous infusion, but not for initial reconstitution (see. Section 6.2. Incompatibilities - Ringer lactate and section 6.6. Application Instructions - Ringer lactate).
For intravenous injection, each vial is to be reconstituted, as mentioned above, and can be applied for at least 3 minutes.
intramuscular
Lidocain NS12% is a suitable vehicle for intramuscular administration, but not for initial reconstitution (see. Section 6.2. Incompatibilities - Lidocain and section 6.6. Application Instructions - Lidocain).
4.3. Contraindications
Sulbactam / cefoperazone is contraindicated in patients with known hypersensitivity to penicillins, sulbactam, cefoperazone or other cephalosporin antibiotic.
4.4. Special warnings and precautions for use
hypersensitivity
There have serious and often fatal hypersensitivity reactions (anaphylaxis) in patients who are administered therapy with beta-lactam or cephalosporin. The occurrence of these reactions are more likely in patients with a history of sensitivity to multiple allergens. If an allergic reaction occurs, the drug should be discontinued and appropriate therapy instituted.
Serious anaphylactic reactions require immediate emergency treatment with epinephrine. If shown to be applied oxygen, intravenous corticosteroids and maintain airway management, including intubation.
Use in liver failure
Cefoperazone is excreted exclusively via the bile. In patients with liver disease and / or biliary obstruction serum half-life of the drug is usually prolonged and urinary excretion increases. Even with severe hepatic dysfunction, therapeutic concentrations of cefoperazone are obtained in bile and only occurs 2-4-fold increase in half-life.
Dose modification may be necessary in cases of severe biliary obstruction, severe hepatic disease or in cases of renal dysfunction coexistent with either of those conditions.
In patients with hepatic dysfunction and concomitant renal impairment should be monitored cefoperazone serum concentrations and therefore, if necessary, the doses to be adapted. In case you do not provide careful monitoring of serum concentrations of cefoperazone dose should not exceed 2 g daily.
General
As with treatment with other antibiotics, and a small proportion of patients treated with cefoperazone, was observed deficiency of vit. The mechanism is probably related to the suppression of the intestinal flora which normally synthesize this vitamin. Patients with high risk were those with a poor diet, malabsorption states (e.g., Cystic fibrosis) and patients on long-term intravenous feeding. In these patients, and in patients on anticoagulant therapy should be monitored for prothrombin time and exogenous vit. K depending on the indication.
As with other antibiotics, and prolonged treatment with sulbactam / cefoperazone may result in overgrowth of resistant organisms. Patients should be monitored closely during treatment. It is recommended that, as with all powerful systemic acting antibiotics, prolonged therapy periodically to monitor organ system dysfunction, this includes renal, hepatic, and hematopoietic systems. This is especially important in neonates, especially when premature, and other infants.
Use in infants
Sulbactam / cefoperazone has been used successfully in infants. Has not been extensively studied in premature infants or neonates. Therefore, before instituting therapy in premature infants and newborns must be weighed against the potential benefits / potential risks (see. Section 5.3. Preclinical safety data - Use in children).
Cefoperazone does not displace bilirubin from binding sites to plasma proteins.
4.5. Drug interactions and other forms of interaction
alcohol
Ingestion of alcohol during treatment with cefoperazone and the fifth day after the interruption is observed reaction characterized by flushing, sweating, headache, and tachycardia. A similar reaction was seen with other cephalosporins and patients should be warned not to drink alcohol during treatment with sulbactam / cefoperazone. For patients requiring artificial feeding orally or parenterally, to avoid solutions containing ethanol.
Interactions with laboratory tests
False-positive reaction for glucose in the urine may occur with tests of Benedict or Fleming.
4.6. Pregnancy and lactation
Use in Pregnancy
Made in reproductive studies in rats at doses up to 10 times higher than human and have revealed no evidence of impaired fertility or teratogenic effects. Sulbactam and cefoperazone cross the placental barrier. However, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human reproduction, this drug can be used during pregnancy only if clearly needed.
Use in nursing
Only small quantities of sulbactam and cefoperazone are excreted in human milk. Although weak in the milk of lactating women, sulbactam / cefoperazone should be administered with caution in them.
4.7. Effects on ability to drive and use machines
Clinical experience shows that it is unlikely sulbactam / cefoperazone impair the patient's ability to drive or operate machines.
4. 8. Adverse reactions
Sulbactam / cefoperazone is generally well tolerated. The majority of adverse drug reactions were mild to moderate and resolved during treatment. In pooled data from comparative and non-comparative clinical trials involving 2500 patients were observed following adverse reactions:
Gastrointestinal: As with antibiotics, the most common adverse reactions were gastrointestinal. The most frequently observed: diarrhea / loose stools - 3.9%, followed by nausea and vomiting - 0.6%.
Dermatological reactions: As with all penicillins and cephalosporins, hypersensitivity manifested by maculopapular rash and hives -0.6% - 0.08%. These reactions often occur in patients with a history of allergies, particularly to penicillin.
Haematology: There was a slight decrease in neutrophils - 0.4% (5/1131). As with other beta-lactam antibiotics, prolonged use may occur reversible neutropenia - 0.5% (9/1696). In some patients, a positive direct test Coombs - 5,5% (15/296) during treatment. There was also a decrease in hemoglobin -0.9% (13/1416) or hematocrit - 0.9% (13/1409), which is in line with published literature on cephalosporins. Seen are transient eosinophilia -3.5% (40/1130) and thrombocytopenia - 0.8% (11/1414) and hypoprothrombinaemia - 3.8% (10/262).
• Miscellaneous: Headache - 0.04%, temperature - 0.5%, pain at the injection site - 0.08%, chills - 0.04%.
Laboratory changes: There have transient increases in liver function tests: ASAT- 5.7% (94/1638), ALT - 6.2% (95/1529), alkaline phosphatase, 2.4% (37/1518) and bilirubin levels: 1.2% (12/1040).
Local reactions: Sulbactam / cefoperazone is well tolerated following intramuscular administration. Sometimes in such an application could follow transient pain. As with other cephalosporins and penicillins, when sulbactam / cefoperazone is administered by an intravenous catheter, it is possible in some patients (0.1%) to develop phlebitis at the infusion site.
After leaving drug market following additional adverse reactions:
General: anaphylactic reaction (including shock);
Cardiovascular: hypotension;
Gastrointestinal: pseudomembranous colitis; Haematopoietic: leukopenia;
Leather / skin appendages: pruritus, syndrome Stevens-Johnson;
Urinary: hematuria; Vascular: vasculitis.
4.9. overdose
There is limited information regarding the acute toxicity of cefoperazone sodium and sulbactam sodium in humans. Overdose are expected to lead to effects that are more pronounced adverse reactions reported for the medicinal product. Must pay attention to the fact that high concentrations of beta-lactam antibiotics in the CNS can cause neurological effects, including seizures. Since cefoperazone, sulbactam and removed from circulation by hemodialysis, these procedures may enhance elimination of the drug from the body if overdosage occurs in patients with impaired renal function.
5. PHARMACOLOGICAL PROPERTIES
5.1. Pharmacodynamic properties
The antibacterial component of sulbactam / cefoperazone is cefoperazone, a third generation cephalosporin, which acts against sensitive actively growing cells by inhibiting biosynthesis of cell wall mukopeptid. Sulbactam does not possess useful antibacterial activity, except against Neisseriaceae and Acinetobacter. However, biochemical studies with cell-free bacterial systems have proved to be an irreversible inhibitor of beta-lactamases produced by resistant to beta-lactam antibiotics of microorganisms.
The potential for sulbactam's preventing the destruction of penicillins and cephalosporins by resistant organisms was confirmed in studies using whole bacterial cells resistant strains in which sulbactam exhibited marked synergy with penicillins and cephalosporins. Since sulbactam also binds with some penicillin-binding proteins, sensitive strains are also often rendered more susceptible to sulbactam / cefoperazone, than just cefoperazone. The combination of sulbactam and cefoperazone is active against all organisms sensitive to cefoperazone. In addition it demonstrates synergistic activity (up to fourfold reduction of the minimum inhibitory concentrations of the combination compared with that of each of its components) in the number of microorganisms, it is the most remarkable in:
Haemophilus influenzae
Bacteroides spp.
Staphylococcus spp.
Acinetobacter calcoaceticus
Enterobacter aerogenes
Morganella morganii
Citrobacter freundii
Enterobacter cloacae
Citrobacter diversus.
Sulbactam / cefoperazone is active in-vitro against a variety of clinically relevant microorganisms.
Gram-positive organisms:
Staphylococcus aureus - penitsilinazoprodutsirashti and penitsilinazoneprodutsirashti strains
Staphylococcus epidermidis
Streptococcus pneumoniae (before Diplococcus pneumoniae) Streptococcus pyogenes (group A beta-hemolytic streptococci) Streptococcus agalactiae (group B beta-hemolytic streptococci)
Most strains of beta-hemolytic streptococci Most strains of Streptococcus faecalis (enterococci)
Gram-negative microorganisms: Escherichia coli Klebsiella spp. Enterobacter spp. Citrobacter spp. Haemophilus influenzae Proteus mirabilis Proteus vulgaris Morganella morganii (before Proteus morganii) Providencia rettgeri (before Proteus rettgeri) Providencia spp.
Serratia spp. (including S. marcescens) Salmonella and Shigella spp.
Pseudomonas aeruginosa and other Pseudomonas spp.
Acinetobacter calcoaceticus
Neisseria gonorrhoeae
Neisseria meningitidis
Bordetella pertussis
Yersinia enterocolitica
Anaerobic microorganisms:
Gram-negative bacilli (including Bacteroides fragilis, other Bacteroides spp. And Fusobacterium spp.)
Gram-positive and Gram-negative cocci (including Peptococcus, Peptostreptococcus and Veillonella spp.)
Gram-positive bacilli (including Clostridium, Eubacterium and Lactobacillus species)
To determine the IPC can be used serial dilutions of sulbactam / cefoperazone in a ratio of 1: 1 by plating on agar or broth. We recommend using a test with sensitivity antibakterilna discs containing 30 mcg sulbactam and 75 mcg cefoperazone in the drive. Laboratory of "susceptible" indicates that the infecting organism is likely to respond to therapy with sulbactam / cefoperazone, a report of "resistant" indicates that the organism would not be affected. A report of "Intermediate" suggests that the organism would be susceptible to sulbactam / cefoperazone, if used in higher dosage or if the infection is confined to tissues or fluids where they reach high antibiotic concentrations.
Recommended are the following control strains for quality control of discs antibacterial sensitivity - 30 mcg / 75 mcg sulbactam / cefoperazone:
Control strain radius area
Acinetobacter spp. ATCC 43498 26-32
Pseudomonas aeruginosa ATCC 27853 22-28
Escherichia coli ATCC 25922 27-33
Staphylococcus aureus ATCC 25923 23-30
5.2. Pharmacokinetic Properties
About 84% of the dose of sulbactam and 25% of the dose of cefoperazone, administered as sulbactam / cefoperazone, is excreted by the kidneys. Most of the remaining dose of cefoperazone is excreted in the bile. After administration of sulbactam / cefoperazone sulbactam average half-life of about 1 hour, while that of cefoperazone is about 1.7 hours. It was found that serum concentrations were proportional to the administered dose. These values are comparable with previously published values for each of the substances administered alone.
The average peak concentrations of sulbactam and cefoperazone after intravenous administration of 2 g sulbactam / cefoperazone (1 g sulbactam, 1 g cefoperazone) after more than 5 minutes were respectively 130.2 and 236.8 mcg / ml.
Write a review
Your Name:Your Review: Note: HTML is not translated!
Rating: Bad Good
Enter the code in the box below:
Related Products